COVID-19 Daily Deaths & Asymptomatic Infections

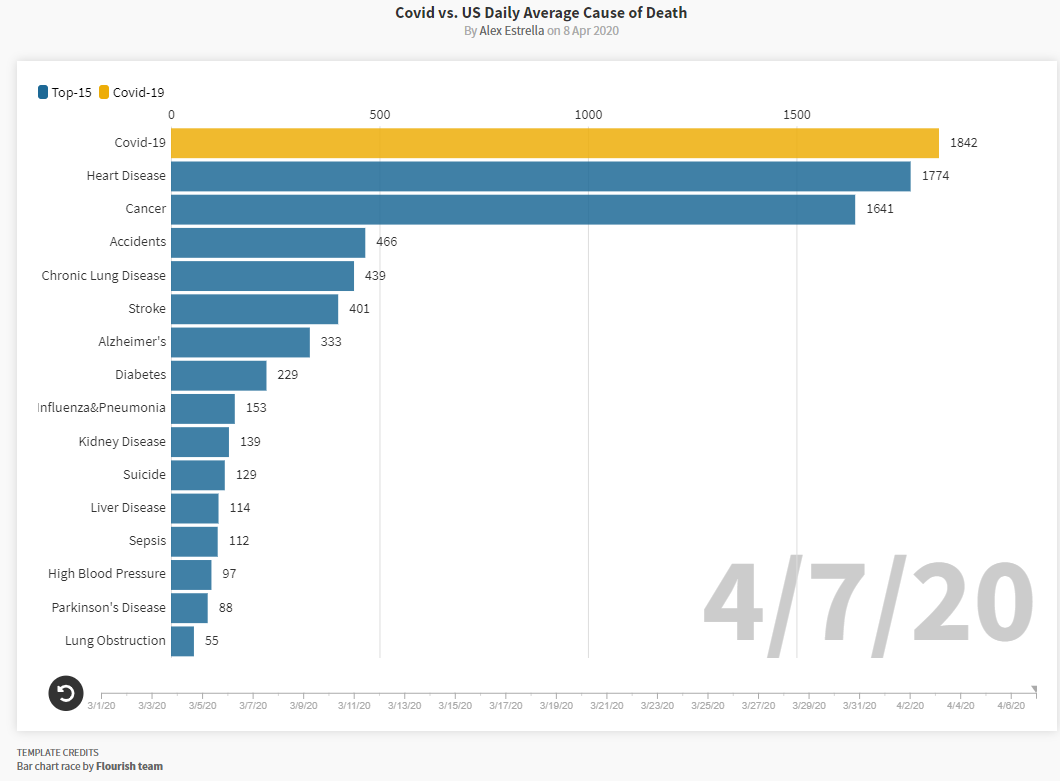
Recent data show why experts were concerned about SARS-CoV-2 (COVID-19 Virus) several months ago, due to its potential for exponential spread. Even now many question whether this infection is more significant than influenza.

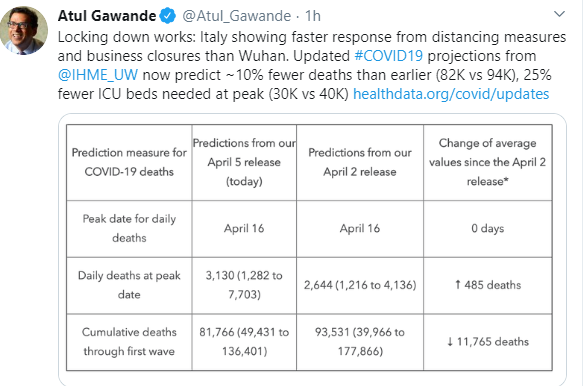
Link: COVID-19 Daily Deaths

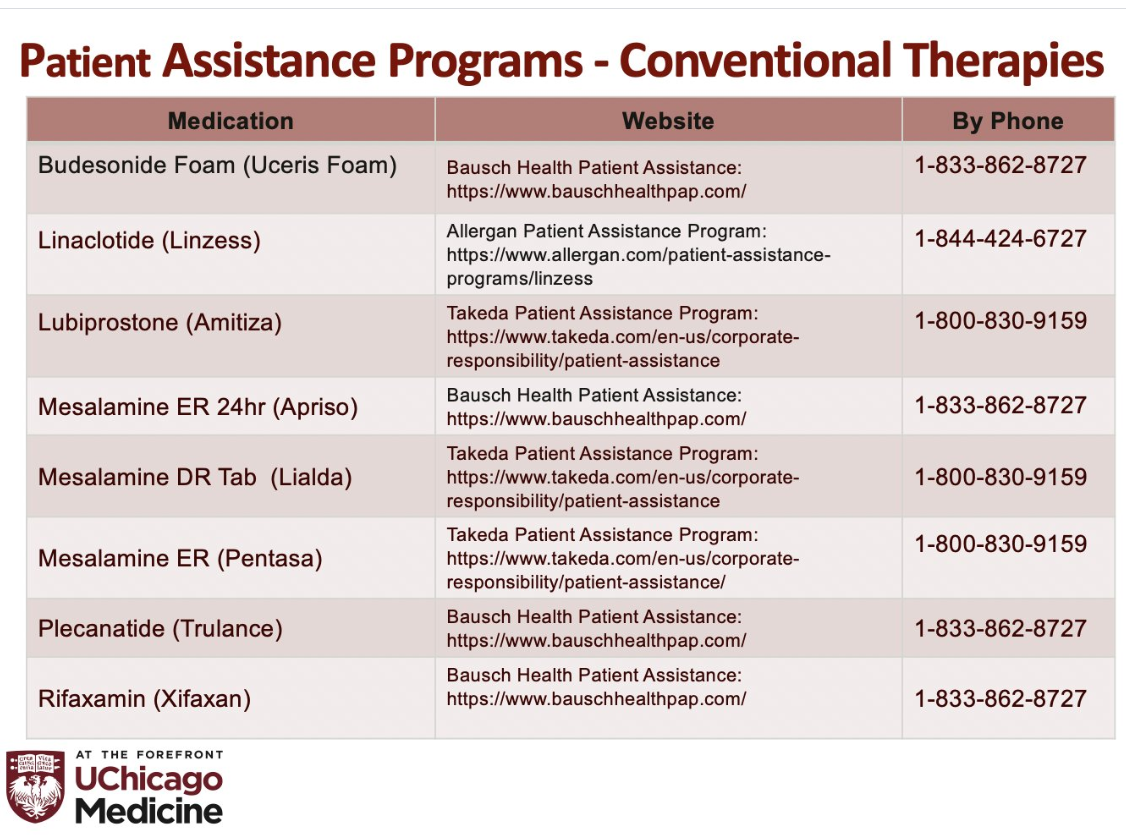
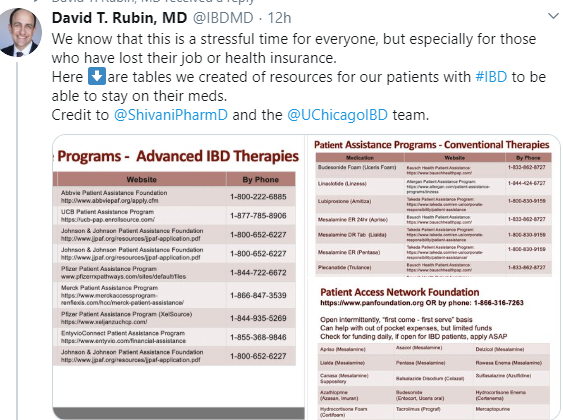
Several screenshots:
NEJM Link: Universal Screening for SARS-CoV-2 in Women Admitted for Delivery

An excerpt:

Between March 22 and April 4, 2020, a total of 215 pregnant women delivered infants at the New York–Presbyterian Allen Hospital and Columbia University Irving Medical Center [NYC] …

Most of the patients who were positive for SARS-CoV-2 at delivery were asymptomatic, and more than one of eight asymptomatic patients who were admitted to the labor and delivery unit were positive for SARS-CoV-2. Although this prevalence has limited generalizability to geographic regions with lower rates of infection, it underscores the risk of Covid-19 among asymptomatic obstetrical patients. Moreover, the true prevalence of infection may be underreported because of false negative results of tests to detect SARS-CoV-2

My take: This study indicates that there are a lot of undetected cases of SARS-CoV-2.


Stony Brook Univeristy’s Innovations to manage COVID-19 Crisis -NEJM: Staying Ahead of the Wave

Some tips:

Related blog posts:


Ups (mostly) and Downs with IBD Epidemiology

Two articles describe both increasing and decreasing trends in the prevalence of inflammatory bowel disease (IBD).

  • Y Ye et al. Inflamm Bowel Dis 2020; 26: 619-25, editorial 626-27
  • M Torabi et al. Inflamm Bowel Dis 2020; 26: 581-90, editorial 591-92 

The first study by Ye et al provides the familiar message that IBD prevalence has been increasing in pediatrics and adults.  This study examined 2 large claims databases.  The Optum database covered ~18 million annually during the study period (total ~57 million from 2007-2017) and Truven covered ~44 million annually (total ~240 million since 1995)

Key findings:

  • Pediatric IBD prevalence increased by 133% from 2007 to 2016: from 33 per 100,000 to 77 per 100,000. Crohn’s disease (CD) was twice as prevalent as ulcerative colitis (UC) in the pediatric population (46 vs 22)
  • Adult IBD prevalence increased by 123% from 2007 to 2016: from 215 per 100,000 to 478 per 100,000. The prevalence rates of CD and UC were similar in adults: 198 vs 181)
  • The Northeast region had the highest prevalence of IBD, followed by Midwest, South and then West.
  • Based on these prevalence data, there are an estimated 58,000 children (2-17) and 1.2 million adults with IBD in U.S.   Or, 1 in 1299 children and 1 in 209 adults.

Limitations:

  • Diagnosis and data derived from claims database
  • Cases can vary significantly based on how sensitive the definition for IBD is in a given study.  In this study, the authors indicate in supplementary material, that the prevalence rates could be doubled in adults if they chose a more sensitive/less specific case definitions.

The second study by Torabi et al, which utilized the Manitoba Epidemiology Database (n=1.2 million) showed a decrease in IBD incidence.  The authors examined 296 small geographic areas (SGAs) and found that many had persistently high IBD incidence rates.

Key findings:

  • The incidence of IBD decreased from 1990 when it was 23.6 per 100,000 to 16.2 per 100,000 in 2012.
  • In the study period (1990-2012), there were 3114 cases of CD and 3499 cases of UC diagnosed in Manitoba

In the discussion, the authors speculate on the reasons for the decline in IBD incidence in an area with high rates of IBD.  Some of the change may be related to changes in the population mix –more immigrants from areas with lower rates of IBD.  In the editorial, it is noted that a recent systematic review (Lancet 2018; 390: 2769-78) indicated that the “incidence of IBD is stabilizing in Western countries.”

My take: There are a lot kids and adults with IBD.  The preponderance of epidemiology studies point to increasing incidence and prevalence.

Related blog posts:

Rock art during “social distancing”

Celiac Studies -Increasing Prevalence (Italy) and Nonadherence Risks

S Gatti et al. Clin Gastroenterol Hepatol 2020; 18: 596-603.   The authors screened 4570 children (5-11 year olds) from 2015-16; this study included 80% of eligible children from two metropolitan areas in Italy.

Key findings:

  • 77 cases of children met diagnostic criteria for celiac disease (54 met criteria and 23 prior known cases)
  • Prevalence in this population, overall, was 1.58% (2015-16); in 1993-95, the adjusted prevalence was 0.88%
  • Celiac disease autoimmunity was noted in 96 .
  • 1960 (43%) had celiac disease associated haplotypes

A Myleus et al. Clin Gastroenterol Hepatol 2020; 18: 562-73.  In this systematic review, 49 studies (out of initial 703) were included in final analysis to determine risk factors and outcomes with nonadherence to treatment with gluten free diet.

Key findings:

  • Large range of adherence rates: 23% to 98% (median rates were 75-87%).
  • Adolescents were at increased risk of non-adherence
  • Children whose parents had good knowledge had higher adherence rates
  • There was not improved adherence over time, despite improvement in palatable gluten-free foods.

One of the other findings in the study was the lack of consensus about what defines strict adherence and how to measure it.

My take: The first study is in agreement with many others which have demonstrated higher prevalence of celiac disease now compared to previously.  The second study shows that adherence with treatment is highly variable and difficult to measure.

Related blog posts:

Screenshot (797)

UNC Campus Pic (Chapel Hill)

Using Spot Urine Sodiums

A recent study (AKN Pedersen et al. JPEN https://doi.org/10.1002/jpen.1593) shows the utility of obtaining urine spot sodiums in patients with an ileostomy. Thanks to Kipp Ellsworth for sharing this reference.

Full link: A Single Urine Sodium Measurement May Validly Estimate 24‐hour Urine Sodium Excretion in Patients With an Ileostomy

Background: Sodium deficiency in patients with an ileostomy is associated with chronic dehydration and may be difficult to detect. We aimed to investigate if the sodium concentration in a single spot urine sample may be used as a proxy for 24‐hour urine sodium excretion.

Design: In this prospective, observational study, we included 16 adult individuals: 8 stable patients with an ileostomy and 8 healthy volunteers with intact intestines

Key finding:

  • There was a high and statistically significant correlation between 24‐hour natriuresis and urine sodium concentrations in both morning spot samples (n = 8, Spearman’s rho [ρ] = 0.78, P = 0.03) and midday spot samples (n = 8, ρ = 0.82, P = 0.02) in the patients with an ileostomy.

My take: In patients with ileostomy (and also short bowel syndrome), periodic urine sodium values (from morning or mid-day) will help detect subclinical sodium depletion.

Related blog posts:


Atlanta Botanical Gardens

Dose Escalation of Ustekinumab & Support Tool “Should I Have IBD Surgery?”

A recent large retrospective study (Effectiveness of Ustekinumab Dose Escalation in Patients with Crohn’s Disease. JE Ollech, et al. Clinical Gastroenterology and Hepatology, EPUB) shows that increasing the frequency of ustekinumab from every 8 weeks to every 4 weeks improves outcomes in those who are not responding optimally. Among 506 patients receiving ustekinumab, 110 had dose escalation.

From abstract:

Results

Following dose interval shortening, the patients’ median HBI [Harvey Bradshaw index] decreased from 4.5 to 3 (P=.002), the median level of CRP decreased from 8 mg/l to 3 mg/l (P=.031), and median level of fecal calprotectin decreased from 378 μg/g to 157 μg/g (P=.57). Among patients who had an HBI >4, a level of CRP ≥5mg/dl, a level of fecal calprotectin >250ug/g, or endoscopic evidence for disease activity before dose interval shortening, after the dose interval was shortened, 28% achieved clinical remission (an HBI score ≤4), 22% had a normal level of CRP (<5 mg/dl), 50% had reduced levels of fecal calprotectin, and 36% achieved endoscopic remission.

My take (borrowed from authors): “Shortening the ustekinumab 90 mg dose interval to 4 weeks for patients with CD who did not respond to doses every 8 weeks improved clinical and biological indices of disease activity. Patients who lose response to the standard dose of ustekinumab might benefit from dose interval shortening, which was effective and safe.”

Related blog posts:

From ImproveCareNow: Should I Have Surgery? A Shared Decision Making Tool  –Recommended for families in working through this difficult treatment decision.

Tiny door on the Atlanta Beltline

NEJM: Compassionate Use of Remdesivir

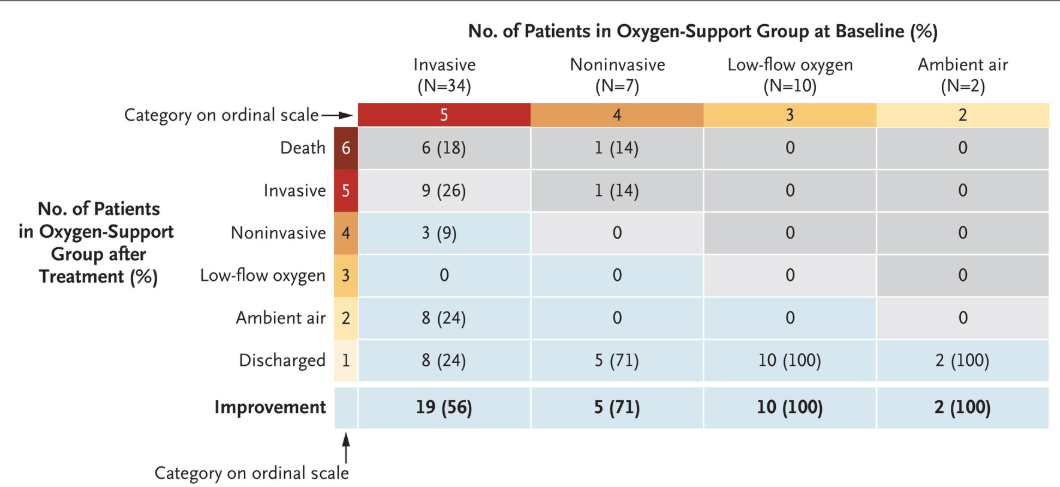
Full report, NEJM, J Grein et al. April 10, 2020, DOI: 10.1056/NEJMoa2007016: Compassionate Use of Remdesivir for Patients with Severe Covid-19

53 of 61 had adequate data for inclusion.  Indications of severe COVID-19: at baseline, 57% required mechanical ventilation and 4 (8%) were receiving ECMO.

With a median follow-up of 18 days, Key findings:

  • 36 patients (68%) had an improvement in oxygen-support class, including 17 of 30 patients (57%) receiving mechanical ventilation who were extubated.
  • 25 patients (47%) were discharged
  • 7 patients (13%) died; mortality was 18% (6 of 34) among patients receiving invasive ventilation and 5% (1 of 19) among those not receiving invasive ventilation.
  • By 28 days of follow-up, the cumulative incidence of clinical improvement, as defined by either a decrease of 2 points or more on the six-point ordinal scale or live discharge, was 84%

My take: Given the severity of the disease, this therapy looks promising. However, the authors note that “measurement of efficacy will require ongoing randomized, placebo-controlled trials of remdesivir therapy.”

For each oxygen-support category, percentages were calculated with the number of patients at baseline as the denominator. Improvement (blue cells), no change (beige) and worsening (gray) in oxygen-support status are shown. Invasive ventilation includes invasive mechanical ventilation, extracorporeal membrane oxygenation (ECMO), or both. Noninvasive ventilation includes nasal high-flow oxygen therapy, noninvasive positive pressure ventilation (NIPPV), or both.


What is Going On With Pouchitis? & No More Handshakes

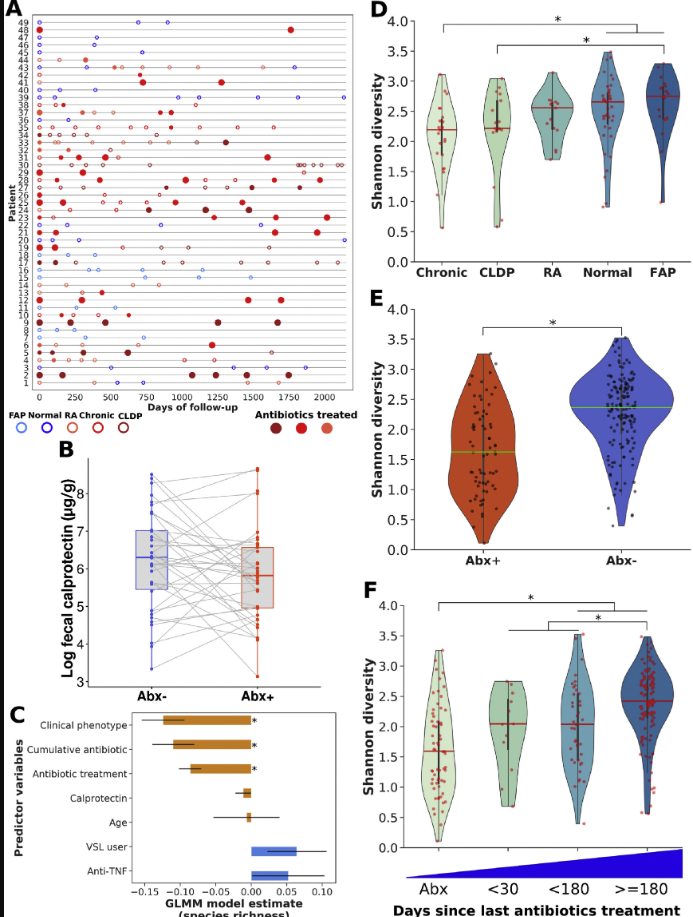
A prospective study (V Dubinsky et al. Gastroenterol 2020; 158: 610-24) followed 49 patients who had undergone pouch surgery for ulcerative colitis or for familial adenomatous polyposis (FAP).

The authors followed multiple parameters including calprotectin, metagenomes/bacterial diversity, antibiotic resistance testing, and virulence factors/toxins. 33 patients received antibiotics for a median of 425 days.  Most patients were treated with a combination of ciprofloxacin and metronidazole.

Full text link: Predominantly Antibiotic-resistant Intestinal Microbiome Persists in Patients With Pouchitis Who Respond to Antibiotic Therapy

Key findings:

  • Pouch phenotype: normal from UC (n=10), recurrent acute pouchitis (n=6), chronic pouchitis and Crohn’s-like disease of the pouch (n=27), and normal from FAP (n=6)
  • 79% of antibiotic-treated patients had a clinical response to each course of antibiotics
  • 89% of those who completed a 4-week course relapsed within 3 months
  • Median calprotectin values decreased by 40% in response to antibiotics
  • Antibiotic treatment reduced disease-associated bacteria including Clostridium perfringens, Ruminococcus gnavus, and Klebsiella pnneumoniae. However, F prausnitzii, a putative anti-inflammatory species, also decreased during antibiotic treatment
  • While antibiotic resistance was noted, these strains had a tendency toward lower potential for virulence and “did not induce secretion of inflammatory cytokines by epithelial cells”

Why do patients become antibiotic-dependent?

“We observed a drastic shift in microbiome composition on antibiotics cessation, characterized by blooms of nonintestinal bacteria, especially those originating from the oral cavity, as well as of opportunistic pathogens. Intestinal colonization by oral bacteria has been associated with UC and Crohn’s disease, and shown to trigger severe intestinal inflammation in germ-free mice…[this] drug-resistant microbiome may be fragile and unable to prevent colonization by exogenous bacteria that are ecologically fitter once antibiotics are discontinued.”

My take: This study provides insight into how antibiotics improve pouchitis; namely, they reduce disease-associated bacteria and promote an antibiotic-resistant microbiome with lower inflammatory potential.

Related blog posts:

Figure 1:

Link:  34 AAP Publications regarding COVID-19 and children

Gastric Electrical Stimulation For Refractory Vomiting, IBD Resources & MMWR COVID-19 Report

A recent yard sign from my wife for neighborhood walkers during the pandemic

P Ducrotte el al (Gastroenterol 2020; 158: 506-14, editorial 461-3) examined the use of an implanted gastric electrical stimulation (GES) in 172 patients in a randomized crossover trial (mean age 45 years).  GES device was implanted and left unactivated until patients were randomized in a double-blind manner to receive stimulation (for 4 months) or not.  Patients had vomiting that was either idiopathic, postsurgical or associated with diabetic gastroparesis (n=72).

Key findings:

  • A significant decrease in vomiting occurred with the device on based on a nonvalidated vomiting score.  During the ON period, vomiting was improved with score of 2.2 compared to vomiting score of 1.8 with device off.  30.6% of patients reported at least a 1 point improvement with device ON compared to device OFF.  However, 16.5% of patients reported improvement with device OFF compared to device ON.
  • Gastric emptying was not accelerated during treatment (device on) compared to no treatment
  • GES was NOT associated with increased quality of life
  • GES was not associated with improved nutritional parameters
  • Adverse effects included pain (n=26) or infection (n=16) at the insertion site of GES; 3 patients required GES removal.

My take (from editorial): “Taking into account the modest magnitude of therapeutic benefit, the cost of the treatment and the potential for adverse events with GES, it seems advisable to exhaust all (symptomatic) therapeutic options” beforehand.

Related blog posts:

IBD Resources (from David Rubin, MD):

COVID-19 March 2020: MMWR Report (Link to report from Bryan Vartabedian 33mail)

  • March 1-28 2020, 84% of hospitalized U.S. patients had underlying diseases -he most common being obesity, hypertension, chronic lung disease, diabetes mellitus, and cardiovascular disease.
  • Hospitalization rates increased with age, with a rate of 0.3 (per 100,000) in persons aged 0–4 years, 0.1 in those aged 5–17 years, 2.5 in those aged 18–49 years, 7.4 in those aged 50–64 years, and 13.8 in those aged ≥65 years


Deconstructing PPI-Associated Risks with Nearly 8 Billion Data Points and More on COVID-19 GI Symptoms (Video)

Link: 22 minute video —COVID-19 and the GI Tract -What We Know Right Now

———————

A recent study (C Ma et al. Gastroenterol 2020; 158: 780-82) used cross-sectional data from the National Ambulatory Medical Care Survey (NAMCS) (2006-2015) with a total 7,872,115,883 weighted observations.  They used this data to evaluate medication exposures and outcomes.

Key findings:

  • There was no association between PPI use and dementia, pneumonia, or intestinal infections.  There was a trend towards intestinal infections (AOR 1.48, CI 0.80-2.71) but this did not reach statistical significance. “Sensitivity analysis showed an association between PPI use and C difficile.”
  • There was an association with chronic kidney disease (CKD) (AOR 1.26); however, this was seen with a multitude of drug classes including statins, calcium channel blockers, and beta-blockers.

Discussion:

  • This study notes that a recent large randomized controlled trial found no statistically significant differences between those receiving PPIs and those receiving placebo except for intestinal infections.
  • With regard to CKD, “it is extremely unlikely that all of these medications increase the risk of CKD, and therefore, it is likely that these findings are due to residual confounding.”

My take: With the exception of C difficile/intestinal infections, this study provides further evidence of the safety of PPIs and a lack of association between these medications and purported PPI-related adverse events.  That said, it is still a good idea to limit use for appropriate indications.

Related blog posts:


Also, IOIBD recommendations for IBD patients and COVID-19 have been published.

Here is link as well:

IOIBD (International Organization for the Study of Inflammatory Bowel Disease) Recommendations (#76) for IBD Patients with Regard to COVID-19:

Full link: IOIBD Update on COVID19 for Patients with Crohn’s Disease and Ulcerative Colitis (3/26/20)


NY Times: How Will We Know When to Reopen the Country? & Timely Tweets

A good read from Aaron Carroll/NY Times: How Will We Know When to Reopen the Country?

Here is an excerpt:

Everyone wants to know when we are going to be able to leave our homes and reopen the United States. That’s the wrong way to frame it.

The better question is: “How will we know when to reopen the country?”…

 A recent report by Scott Gottlieb, Caitlin Rivers, Mark B. McClellan, Lauren Silvis and Crystal Watson staked out some goal posts.

  • Hospitals in the state must be able to safely treat all patients requiring hospitalization, without resorting to crisis standards of care.
  • A state needs to be able to test at least everyone who has symptoms.
  • The state is able to conduct monitoring of confirmed cases and contacts.
  • There must be a sustained reduction in cases for at least 14 days…

These four criteria are a baseline…Until we get a vaccine or effective drug treatments, focusing on these major criteria, and directing efforts toward them, should help us determine how we are progressing locally, and how we might achieve each goal.

Related blog posts/links: