What is An Emulsifier and Are They Safe in Our Diets?

Two recent articles examine emulsifiers and their potential impact on the GI tract and beyond.

Levine et al provide a good overview of the topic of emulsifiers. Key points:

  • Emulsifiers allow “the mixing of water and and water-soluble agents with fats and fat-soluble agents that is they possess both hydrophilic and lipophilic properties”
  • The FDA “has been responsible for approving the use of all direct food additives” (n=~3000) and “for regulatory purposes, [the FDA excluded] some substances that were generally regarded as safe (GRAS) (n=~450)…Precisely how some emulsifiers gained GRAS status is unclear.
  • “Lecithin” is derived from the Greek name for egg yolk (lekithos). “Over the years the use of the term “lecithin” has been taken to include various mixtures of different phospholipids” (not just phosphatidylcholine).
  • Lecithin can provide the substrate “for the production of trimethylamine N-oxide (TMAO)…linked to cardiac events and cardiovascular inflammation.”
  • “The list of emulsifiers that are widely used, but not considered GRAS, most notably include polysorbate 80 (p80), carboxymethylcellulose (CMC) and carrageenan…these emulsifiers have been linked to the disruption of the microbiota and gut mucosal lining…In addition, low-grade inflammation [has been] associated with consumption of emulsifying agents such as CMC and p80” [in mouse models].
  • The International Organization for the Study of Inflammatory Bowel Disease (IOIBD) has recommended that IBD patients “limit consumption of certain commonly encountered synthetic emulsifiers, specifically carboxymethylcellulose (E466/cellulose gum) and polysorbate 80 (E433) [which] are present in many processed foods, such as ice cream. The group also recommends a decrease in foods containing carrageenan”

In the second study by Chassaing et al with 16 healthy adults, the authors studied the effects of CMC in those with an emulsifier-free diet (n=9) or an identical diet enriched with CMC (n=7).

Key findings:

  • Relative to control subjects, CMC consumption modestly increased postprandial abdominal discomfort and perturbed gut microbiota composition in a way that reduced its diversity
  • CMC-fed subjects exhibited changes in the fecal metabolome, particularly reductions in short-chain fatty acids and free amino acids
  • 2 subjects consuming CMC who exhibited increased microbiota encroachment into the normally sterile inner mucus layer, a central feature of gut inflammation, as well as stark alterations in microbiota composition

My take: The dramatic increase in the prevalence of IBD over the past 50 years indicates a strong influence of environment factors, particularly diet. Determining which of these factors are most important will be challenging. These articles indicate that some emulsifiers could be contributing to GI tract inflammation and non-GI tract inflammation as well.

The challenges with identifying dietary factors relate to difficulties with using randomized controlled trials (especially eliminating delicious foods) to assess the impact over a long period of follow-up.

Related blog posts:

New Therapy for Crohn’s Disease: Mirikizumab

Because our office is one of the centers participating in a mirikizumab study for adolescents, I was particularly interested in seeing the published results of a phase 2 study in 191 adults.

BE Sands et al. Gastroenterol 2022; 162: 495-508. Open Access: Efficacy and Safety of Mirikizumab in a Randomized Phase 2 Study of Patients With Crohn’s Disease

Summary Video Link (worth a watch!): Summary of Mirikizumab Study (4:25 minutes)

Background: “Mirikizumab (LY3074828) is a humanized immunoglobulin G4 (IgG4)–variant monoclonal antibody that binds specifically to the p19 subunit of IL23 and has demonstrated efficacy in psoriasis and ulcerative colitis, and is currently in phase 3 testing for psoriasis, ulcerative colitis, and CD. We evaluated the efficacy and safety of mirikizumab for the treatment of patients with moderately-to-severely active CD”

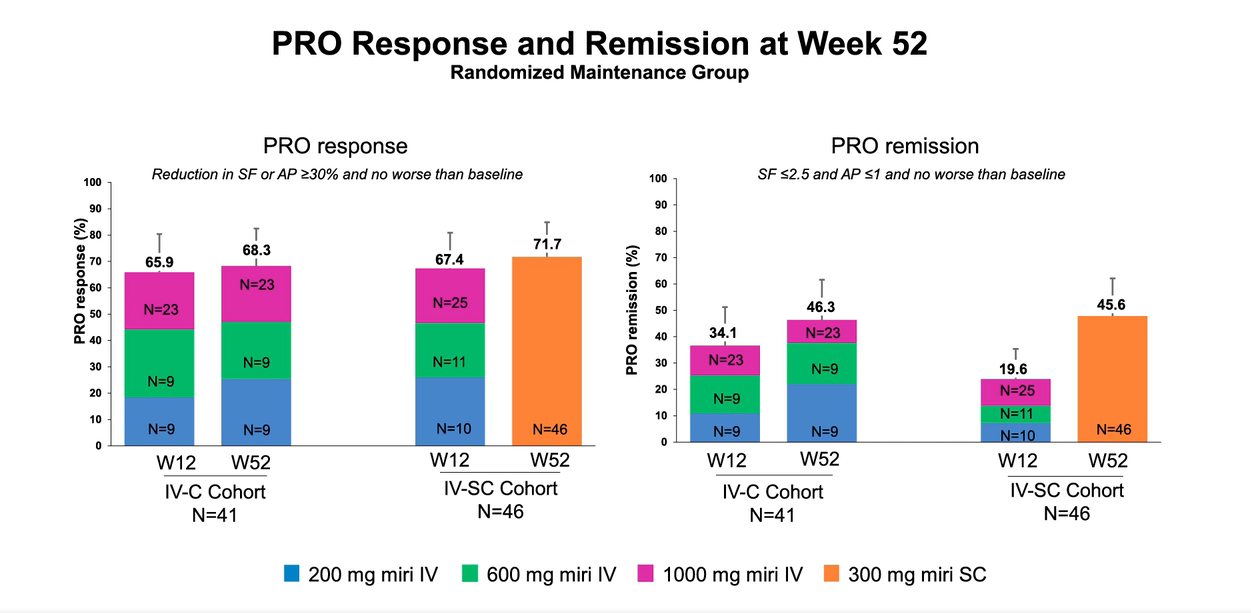
Methods: Patients (N = 191) were randomized (2:1:1:2) to receive placebo (PBO), 200, 600, or 1000 mg mirikizumab, administered intravenously (IV) every 4 weeks. Patients who received mirikizumab and achieved ≥1 point improvement in Simple Endoscopic Score-CD at Week 12 (rerandomized maintenance cohort) were rerandomized to continue their induction IV treatment (combined IV groups [IV-C]) or receive 300 mg mirikizumab subcutaneously (SC) every 4 weeks. Nonrandomized maintenance cohort included endoscopic nonimprovers (1000 mg) and PBO patients (PBO/1000 mg) who received 1000 mg mirikizumab IV from Week 12. The primary objective was to evaluate superiority of mirikizumab to PBO in inducing endoscopic response (50% reduction from baseline in Simple Endoscopic Score-CD) at Week 12.

**approximately two thirds of participants had received biologic therapy and approximately half of all patients in this trial having experienced at least 1 biologic failure

Key findings:

  • At Week 12, endoscopic response was significantly higher for all mirikizumab groups compared with placebo (PBO) (200 mg: 25.8%, P = .079; 600 mg: 37.5%, P = .003; 1000 mg: 43.8%, P < .001; PBO: 10.9 %). 
  • Endoscopic response at Week 52 was 58.5% (24/41) and 58.7% (27/46) in the IV-C (combined IV groups) and SC (subcutaneous) groups , respectively. See 4th and 6th slides below which show that those with response at 12 weeks continued with response at 52 weeks.
In the Non-Randomized group which included non-improvers and placebo, they received
the highest dose, 1000 mg. A significant number of non-improvers responded at week 52.

My take: In this study of adults, with moderate to severe Crohn’s disease, Mirikizumab showed good efficacy and safety at both 12 weeks and 52 weeks. Because about half of the participants were biologic failures, this indicates that this agent shows promise in those with refractory disease.

NASPGHAN 2021 Nutrition Highlights

Thanks to Kipp Ellsworth for forwarding this link:

Nutrition for IBD website: NASPGHAN 2021 Nutritional Highlights

On this website: “Four presentations/lectures were released at the Nutritional Therapy for IBD Virtual Booth that provide a comprehensive review and update of the latest information regarding the use of EEN and therapeutic diets in the management of IBD”

Why Do We Need Dietary Therapies for IBD

Presenter: Lindsey Albenberg, DO

Dr. Lindsey Albenberg, a clinician and researcher from Children’s Hospital of Philadelphia, describes the rapidly increasing incidence of IBD and its relationship to diet, microbiome and the immune system. She reviews the rationale and science supporting the use of dietary therapy to compliment drug therapy as an avenue to potentially achieve higher, more sustainable and possibly safer levels of remission long term in pediatric patients.

The Crohn’s Disease Exclusion Diet Updates: December 2021

Presenter: Rotem Sigall Boneh, RD. Rotem Sigall Boneh, RD, a primary researcher and developer of CDED, provides an overview of the accumulating data with CDED in combination with PEN, including the newly published results of adult data with important endoscopic findings and further shares real world experience and application of nutritional therapy.

IBD Anti-inflammatory Diet or IBD-AID: Proof of Concept

Presenter Ana Maldonado-Contreras, MSc, PhD. Dr. Ana Maldonado-Contreras, a lead researcher in IBD-AID explains the relationship between diet, microbiome and immune function with the design and rational of IBD-AID to manipulate the microbiome. She shares the recently published data of the impact of IBD-AID on the microbiome and cytokine levels specific to food components.

Nutritional Therapy: Perioperative + Complicated Crohn’s Disease

Presenter Andrew S. Day, MB, ChB, MD, FRACP, AGAF

At the NTforIBD Nutritional Symposium prepared for NASPGHAN2021, Professor Day provides insight into the important role of EEN, an underutilized option to both induce remission and improve outcomes in complicated and peri-operative patients.

IBD Shorts: Fecal Calprotectin in UC & Medication Withdrawal, Outcome of Biosimilar Reverse Switches, Vedolizumab after Anti-TNF Therapy

TW Stevens et al. Inflamm Bowel Dis 2021; 19: 2333-2342. Open Access. Diagnostic Accuracy of Fecal Calprotectin Concentration in Evaluating Therapeutic Outcomes of Patients With Ulcerative Colitis

Key finding: A post hoc analysis of data from a phase 4 trial (the MOMENTUM trial) found that, even in patients (n=593 at week 8, n=305 at week 52) with complete endoscopic healing of UC, FC concentration can be used to discriminate patients with ongoing microscopic inflammation from patients with histologic remission.  The optimal FC cut-off concentrations for identification of patients with histologic remission were 75 μg/g at week 8 and 99 μg/g at week 52.

A Cassinotti et al. Clin Gastroenterol Hepatol 2021; 19: 2293-2301. Noninvasive Monitoring After Azathioprine Withdrawal in Patients With Inflammatory Bowel Disease in Deep Remission

Key finding: In this prospective study, 57 patients in deep remission stopped azathioprine after a median of 7 years. 26 (46%) relapsed within a median of 15 months. Fecal calprotectin (FC) levels were >50 mcg/g in all patients with relapse (FC specificity 100%) but the sensitivity was only 50%. Thus, having a normal FC does not preclude relapse but elevated FC is associated with relapse.

S Mahmmod et al. Inflamm Bowel Dis 2021; 27: 1954-1962. Outcome of Reverse Switching From CT-P13 to Originator Infliximab in Patients With Inflammatory Bowel Disease
In this retrospective study, 75 patients, 9.9% of all patients, who had been changed from originator infliximab to a biosimilar had clinical worsening. Key finding: Improvement of reported symptoms was seen in 73.3% of patients after reverse switching back to originator infliximab; alsor 7 out of 9 patients (77.8%) with loss of response regained response

J Kim et al. Inflamm Bowel Dis 2021; 27: 1931-1941. Clinical Outcomes and Response Predictors of Vedolizumab Induction Treatment for Korean Patients With Inflammatory Bowel Diseases Who Failed Anti-TNF Therapy: A KASID Prospective Multicenter Cohort Study

Key finding: Clinical remission rates with vedolizumab among patients with CD (n=80) and patients with UC (n=78) were 44.1% and 44.0%. Among patients with UC, the endoscopic remission rate was 32.4%

Favorite Posts of 2021

I am happy to say that this is the last nightcall that I will have this year!

Today, I’ve compiled some of my favorite posts from the past year. I started this blog a little more than 10 years ago. I am grateful for the encouragement/suggestions from many people to help make this blog better. Also, I want to wish everyone a Happy New Year.

GI:

IBD:

LIVER:

Nutrition:

Other Topics:

Thanks to Jennifer

Preclinical Disease Detection of Inflammatory Bowel Disease

Recent articles indicate the possibility of preclinical disease detection of inflammatory bowel disease; perhaps this is analagous to the “precrime’ detection in The Minority Report which allowed the police to arrest people before they committed their crime.

D Bergemalm et al. Gastroenterol 2021; 161: 1526-1539. Open Access: Systemic Inflammation in Preclinical Ulcerative Colitis

In this study from Sweden, the authors used biobanked plasma samples from 72 individuals with ulcerative colitis (UC) and matched healthy controls (n=140). Then the findings were validated in an inception cohort (n=101 with UC and 50 healthy controls. In addition, a cohort of heathy twin siblings of patients with UC (n=41) were matched with healthy controls (n=37).

Key findings:

  • Six proteins (MMP10, CXCL9, CCL11, SLAMF1, CXCL11 and MCP-1) were up-regulated (P < .05) in preclinical ulcerative colitis compared with controls
  • MMP10, CXCL9, CXCL11, and MCP1, but not CCL11 and SLAMF1, were significantly up-regulated among the healthy twin siblings. This up-regulation is triggered by exposure to genetic and early environmental factors.

The discussion elaborates on the role of these proteins.

  • “MMP10 is classified as a stromelysin. Upregulated levels of stromelysin have been detected in inflamed segments of the colon from patients with ulcerative colitis….The observed preclinical upregulation of MMP10 [thought to promote wound healing] in plasma might indicate that endogenous pathways for wound healing are up-regulated several years before clinically overt ulcerative colitis to counteract disease progression and maintain mucosal homeostasis”
  • “Eotaxin (CCL11) is a potent chemoattractant of monocytes…eosinophilic-driven inflammation represents an early element in the pathogenesis of ulcerative colitis”
  • “CXCL9 and CXCL11 has been observed previously in inflamed colonic tissue specimens and blood from patients with ulcerative colitis… Both chemokines are regulated by IFN-gamma and attract CXCR3-positive CD4þ T cells and natural killer cells to the inflammatory site”

My take: This study shows up-regulation of 6 plasma proteins indicating activation of both pro-inflammatory and tissue-repairing pathways several years before clinically overt UC. It offers hope of intervention to prevent the development of UC.

Related study: S-H Lee et al. Gastroenterol 2021; 161: 1540-1551. Open Access: Anti-Microbial Antibody Response is Associated With Future Onset of Crohn’s Disease Independent of Biomarkers of Altered Gut Barrier Function, Subclinical Inflammation, and Genetic Risk

In this study, the authors measured host serum antibody response to 6 microbial antigens at enrollment (Prometheus enzyme-linked immunosorbent assay test: anti-Saccharomyces cerevisiae antibodies immunoglobulin A/immunoglobulin G, anti-OmpC, anti-A4-Fla2, anti-FlaX, anti-CBir1) and derived the sum of positive antibodies (AS).

Key finding:

“High baseline AS (≥2) (43% of cases, 11% of controls) was associated with higher risk of developing CD (adjusted odds ratio, 6.5; 95% confidence interval, 3.4–12.7; P < .001). Importantly, this association remained significant when adjusted for markers of gut barrier function, fecal calprotectin, C-reactive protein, and CD-polygenic risk score, and in subjects recruited more than 3 years before diagnosis. Causal mediation analysis showed that the effect of high AS on future CD development is partially mediated (42%) via preclinical gut inflammation.

Dietary Therapy for Adults with Crohn’s Disease

H Yanai et al. The Lancet 2021; The Crohn’s disease exclusion diet for induction and maintenance of remission in adults with mild-to-moderate Crohn’s disease (CDED-AD): an open-label, pilot, randomised trial https://doi.org/10.1016/S2468-1253(21)00299-5

In this open-label trial of adults with mild-to-moderate biologic naive Crohn’s disease, key findings:

  • At week 6, 13 (68%) of 19 patients in the CDED plus partial enteral nutrition group and 12 (57%) of 21 patients in the CDED group had achieved clinical remission (p=0·4618)
  • Among the 25 patients in remission at week 6, 20 (80%) were in sustained remission at week 24 (12 patients in the CDED plus partial enteral nutrition group and eight in the CDED alone group)
  • 14 (35%) of 40 patients were in endoscopic remission at week 24 (eight patients in the CDED plus partial enteral nutrition group and six in the CDED alone group)

My take: Dietary therapy may be effective option for motivated adult patients with Crohn’s disease.

Related blog posts:

Correlating Calprotectin with Disease Severity in Pediatric IBD

E Crawford et al. JPGN Reports 2021; 22 – Issue 4 – p e129. Open Access: Association of Fecal Calprotectin With Endoscopic and Histologic Activity in Pediatric Inflammatory Bowel Disease
This retrospective study used data from 331 patients (n=107 with IBD). Fecal calprotectin (FC) was done between 30 days and 1 day before colonoscopy.

Key findings:

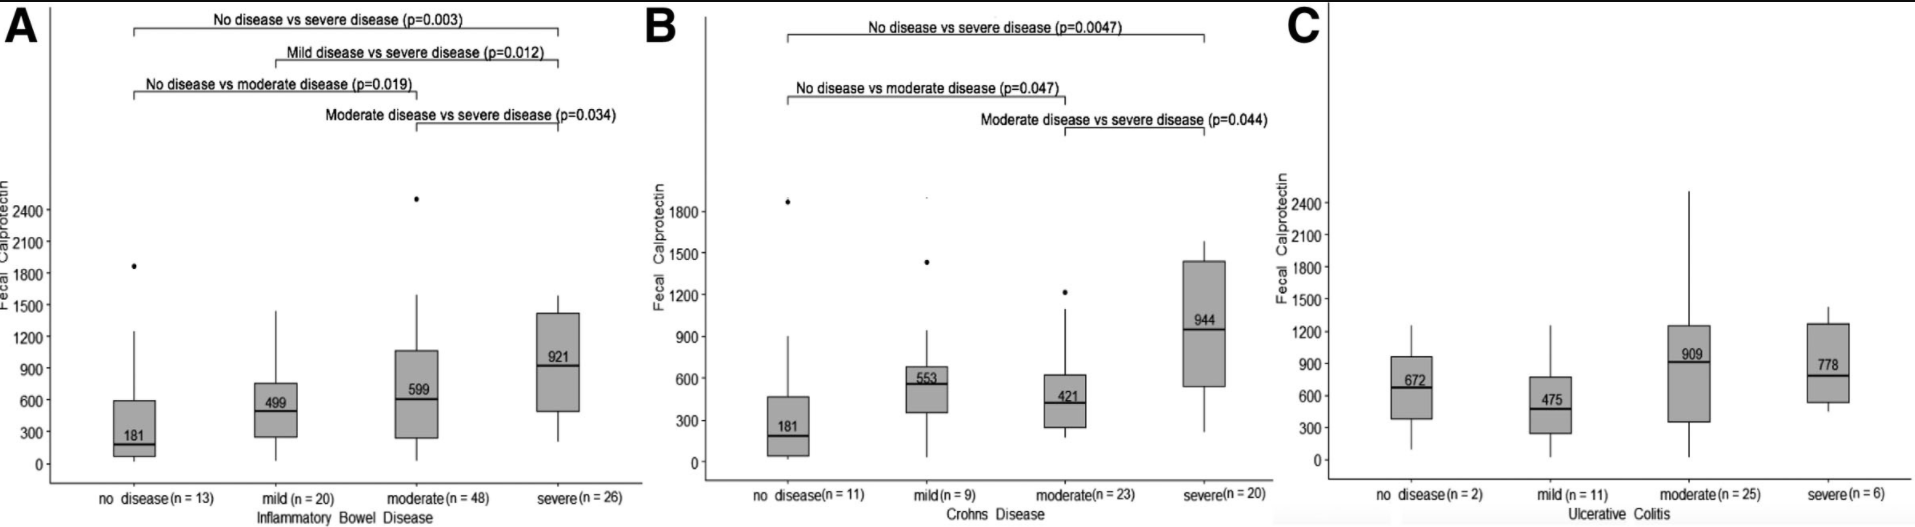
  • Correlation with endoscopy: median FC was lowest for all IBD patients with no active disease (181 μg/g) and highest in severe disease (921 μg/g), with significant difference between no disease and moderate and severe disease (P = 0.019, 0.003), and between mild and severe disease (P = 0.012)
  • Correlation with histology: median FC was lowest with no active disease (328 μg/g) and highest in severe disease (895 μg/g), with significant difference between no disease and moderate and severe disease (P = 0.021, 0.018)
  • The control population had median FC of 35.5 compared to 181 μg/g for the IBD population in endoscopic remission (P = 0.018).

My take: Calprotectin levels are particularly helpful as a screen for IBD (probably using threshold of at least 120) and its use to monitor clinical response. This study shows it has some utility in predicting disease severity.

Figure 1: Fecal calprotectin association with endoscopic disease severity of IBD
(A), Crohn’s disease (B) and ulcerative colitis (C). IBD = inflammatory bowel disease.

Biologic Treatment Effectiveness for Esophageal Crohn’s Disease

J Lui et al. Inflamm Bowel Dis 2021; 27: 1544-1547. The Use of Biologics for the Treatment of Esophageal Crohn Disease

In this retrospective review (1998-2018), the authors identified 39 patients with esophageal Crohn disease (ECD) who met inclusion criteria.

Key findings:

  • 35 (92%) had a clinical response to treatment and 21 (55%) went into clinical remission
  • ECD seems to be associated with more disabling intestinal CD phenotypes. Of the 39 patients, 10 (26%) had stricturing phenotype and 21 (54%) had penetrating phenotype; 19 (49%) had perianal disease
  • “Initial treatment after diagnosis with anti-TNFalpha agents compared to other biologics was associated with greater improvement in clinical (97% vs 71%; P=0.02) and endoscopic response (95% vs. 40%; P<0.01) and in clinical remission (64.5% vs. 14.2%; P=0.01).”
  • Initial treatment with an anti-TNFalpha agent was initial treatment in 18 patients with ECD; 14 had an inflammatory, 3 had a stricturing, and 1 had a fistulizing phenotype.

While this study showed better response to anti-TNFalpha agents compared to other biologics (eg. anti-IL-12/IL-23 agents), this may be due to a selection bias as other biologics are often used as a second-line treatment and are selected more often in refractory disease.

My take: Esophageal Crohn’s disease is a rare diagnosis and appears associated with more severe disease.

Chesapeake and Ohio Canal National Historic Park (near Washington D.C.)

Vedolizumab vs Adalimumab: Histology Outcomes from Varsity Trial

L Peyrin-Biroulet et al. Gastroenterol 2021; Open Access DOI:https://doi.org/10.1053/j.gastro.2021.06.015. Histologic Outcomes With Vedolizumab Versus Adalimumab in Ulcerative Colitis: Results From An Efficacy and Safety Study of Vedolizumab Intravenous Compared to Adalimumab Subcutaneous in Participants With Ulcerative Colitis (VARSITY)

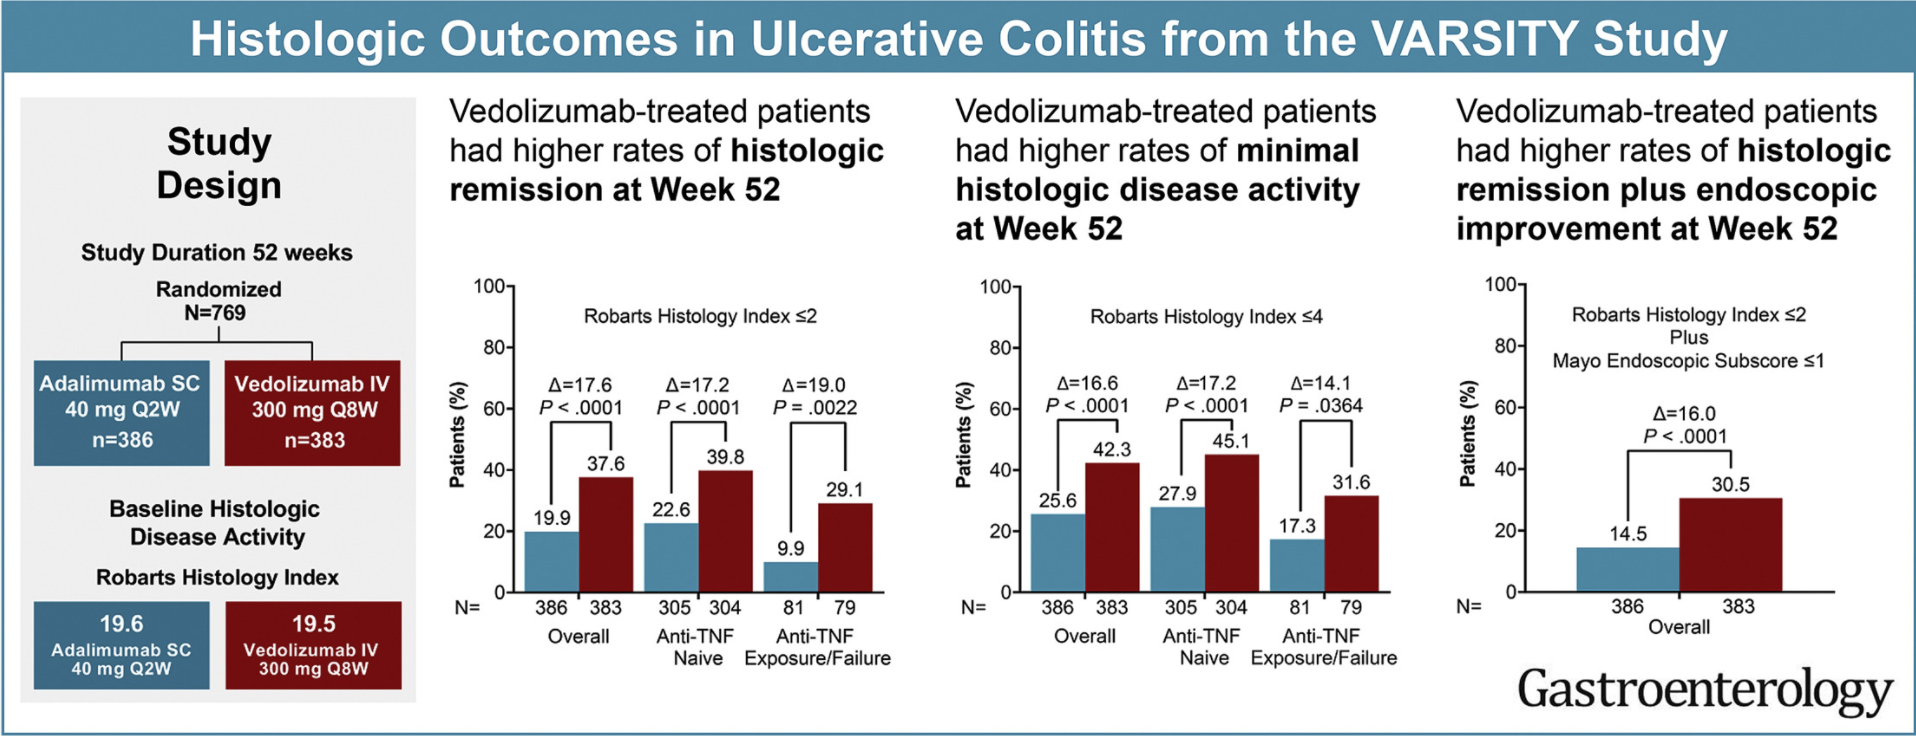
In total, 769 patients received vedolizumab (n = 383) or adalimumab (n = 386). Geboes Index and Robarts Histopathology Index (RHI) scores were used to assess prespecified histologic exploratory end points of histologic remission (Geboes <2 or RHI ≤2) and minimal histologic disease activity (Geboes ≤3.1 or RHI ≤4) at weeks 14 and 52.

Key findings:

Vedolizumab induced greater histologic remission than adalimumab:

  • week 14: Geboes: 16.7% vs 7.3%, RHI: 25.6% vs 16.1%
  • week 52: Geboes: 29.2% vs 8.3%, RHI: 37.6% vs 19.9%
  • Histologic outcomes were generally better in anti–TNF-naïve vs -failure patients

My take: This study shows that histologic outcomes with vedolizumab, similar to clinical outcomes, were better than with adalimumab. Some of this difference could be due to the trail design which did not allow optimization of adalimumab dosing.

Related posts: